 By

The short answer is more interesting than a yes or a no.
Sleep problems are clearly associated with worse sperm — lower counts, lower concentration, reduced motility. That link is reasonably well established. But when researchers looked specifically at semen volume, the amount of fluid you actually ejaculate, they found no significant association.
So if the thing you’re worried about is volume, the honest answer is that sleep is probably not your explanation. If what you’re worried about is fertility, sleep matters quite a lot. Those are different questions, and most articles on this topic collapse them.
What the sleep data actually show
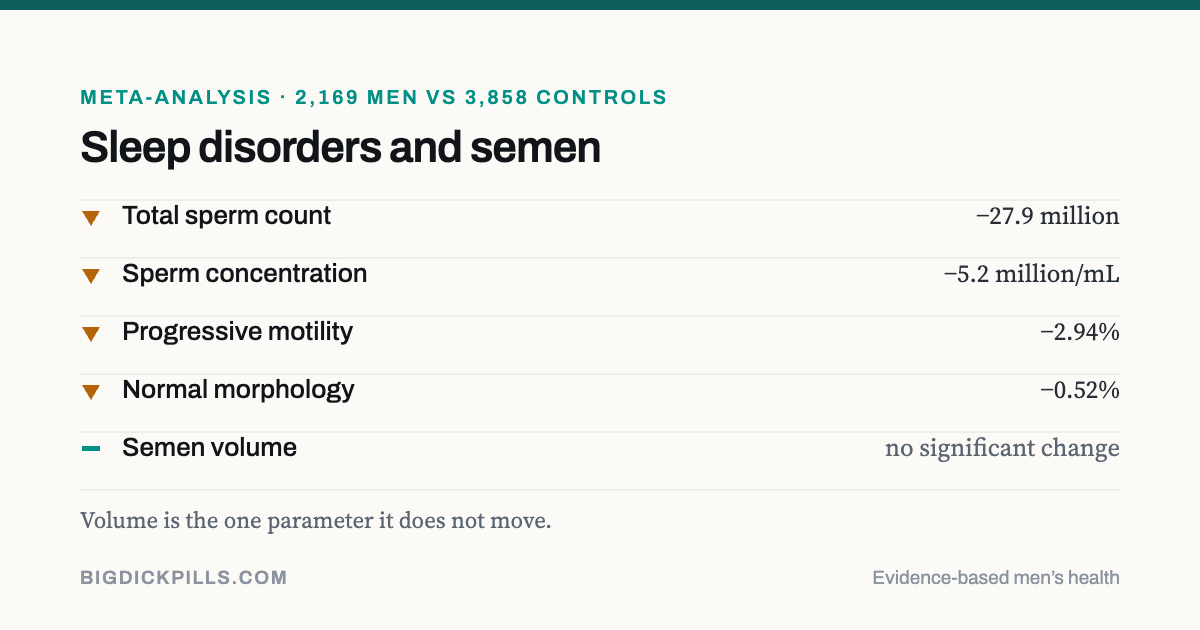
A 2022 systematic review and meta-analysis in Frontiers in Physiology pooled eight studies comparing men with sleep disorders against controls — 2,169 men with sleep disorders and 3,858 without.
Men with sleep disorders had:
| Parameter | Difference |
|---|---|
| Total sperm count | −27.91 million (p < 0.001) |
| Sperm concentration | −5.16 million/mL (p = 0.02) |
| Progressive motility | −2.94% (p = 0.01) |
| Normal morphology | −0.52% (p < 0.001) |
| Semen volume | No significant association |
| Testosterone, FSH, LH | No significant association |
A 28-million drop in total sperm count is not trivial. For context, the WHO’s 2021 lower reference limit for total sperm number is 39 million per ejaculate.
The review also picked out specific patterns:
- Six hours of sleep or less was associated with reduced normal sperm morphology
- Going to bed after midnight was linked to lower total sperm count and reduced progressive motility
- Shift work was associated with lower sperm concentration
The proposed mechanism is circadian disruption rather than hormonal — which fits, given the review found no significant effect on testosterone, FSH or LH.
The caveat that matters
Most of the included studies were cross-sectional. That means they measured sleep and semen at the same moment and looked for correlation. They cannot establish that poor sleep caused the worse parameters. Men with sleep disorders differ from men without them in many ways — weight, shift work, stress, alcohol, underlying illness — and any of those could drive the association.
This is a real limitation, not a formality. It is the difference between “these things travel together” and “fixing one fixes the other,” and the available data support the first claim considerably better than the second.
What about stress?
Here the evidence is thinner, and I want to be straight about that rather than dress it up.
Stress and semen quality have been studied repeatedly, mostly in cross-sectional and cohort designs, and the results are mixed. Several studies report associations between higher perceived or psychosocial stress and poorer semen parameters. Others find little. The literature has the hallmarks of a field where publication bias, inconsistent stress measurement instruments, and confounding all bite hard.
What can be said with more confidence:
Stress has an obvious short-term route to ejaculate volume that has nothing to do with sperm production. Sperm take roughly 74 days to develop, so nothing that happened this week is reflected in this week’s sperm count. But ejaculation itself is a neurological event involving sympathetic nervous system activity, and stress and anxiety plausibly affect it directly and immediately. That’s a different mechanism operating on a different timescale.
Stress affects ejaculation frequency, which affects volume. This is probably the largest real-world pathway and it’s almost never mentioned. Stress changes how often people have sex. Frequency of ejaculation is the single biggest determinant of the volume of any given ejaculate. A stressed man with a smaller ejaculate may simply be having sex more often than usual, or less, and seeing the arithmetic of that.
What we cannot say is that a given amount of stress reduces semen volume by a given amount. Anyone who tells you that number is inventing it.
The thing that actually determines volume
If you take one mechanism away from this page, make it this one: volume is mostly a function of time since your last ejaculation.
Semen accumulates between ejaculations. The same man, measured a day after his last ejaculation and again after four days, will produce noticeably different volumes with nothing else changed. This is why semen analysis instructions specify an abstinence window — commonly two to seven days — and why any comparison you make between two ejaculations at different intervals is meaningless.
Most men who believe their volume has dropped are comparing across different intervals without realizing it. Before looking for a medical explanation, it’s worth ruling out the arithmetic one.
What is worth doing anyway
Even on cross-sectional evidence that can’t prove causation, the sleep advice here is unusually low-risk, because it’s the same advice that follows from everything else known about sleep:
- Aim for more than six hours; the morphology signal appeared at six or fewer
- Get to bed before midnight where your schedule allows — late bedtime showed up as an independent factor, separate from total duration
- Take shift work seriously as a health exposure if you’re trying to conceive, and raise it with your doctor
- Get sleep apnea assessed if you snore heavily, wake unrefreshed, or your partner reports you stop breathing — it’s common, treatable, and independently linked to low testosterone
None of that will change your ejaculate volume, on the evidence available. It may well improve the parameters that matter for fertility, and it will improve a good deal else besides.
When to stop troubleshooting and get a semen analysis
A semen analysis costs relatively little and replaces all this speculation with numbers. It’s worth doing if:
- You’ve been trying to conceive for twelve months without success, or six months if your partner is over 35
- Volume dropped suddenly and stayed down, especially with cloudy urine after sex
- Volume changes began after a new medication, particularly an alpha-blocker
- Low volume comes alongside low libido, fatigue, or erectile difficulty
Remember that one sample is a snapshot of a variable system. Clinicians generally want two, several weeks apart, before concluding anything.
Sources
- Wang C, et al. “Sleep disorders and male reproductive health: a systematic review and meta-analysis.” Frontiers in Physiology, 2022. Full text
- World Health Organization. WHO Laboratory Manual for the Examination and Processing of Human Semen, 6th edition (2021). Lower reference limits (PDF)
- American Urological Association / American Society for Reproductive Medicine. Diagnosis and Treatment of Infertility in Men: AUA/ASRM Guideline (2020, amended 2024). Guideline
This article is for information only and is not medical advice. It cannot account for your individual circumstances. Talk to a doctor about your own situation.